
Surgical & OT Essentials: A Complete Guide to Surgical Instruments, OT Supplies & Consumables

Introduction: In the OT, the Smallest Detail Can Matter Most
A successful operation depends on much more than the surgeon’s skill. The right surgical instruments, sterile supplies, consumables, equipment and a well-prepared operating theatre all have to work together at exactly the right moment.

Imagine a routine procedure is underway and a required clamp is missing, a sterile pack has compromised packaging, or a commonly used consumable has unexpectedly gone out of stock. None of these problems sounds dramatic when viewed individually. Inside an operating theatre, however, even a small supply-chain or preparation failure can create delays, increase stress and affect efficiency.

That is why surgical procurement should not be treated simply as “buying medical products.” It is about creating a dependable clinical system.

From forceps and scissors to drapes, gowns, sutures, surgical blades and sterilization supplies, every item has a role. The best OT inventory is not necessarily the largest one—it is the one that is appropriate, traceable, sterile when required, readily available and easy for the clinical team to use correctly.

This guide explains the essentials of surgical instruments, OT supplies and consumables and offers practical insights for hospitals, clinics, ambulatory surgery centres and healthcare procurement teams.

What Comes Under Surgical & OT Essentials?

An operating theatre requires several interconnected product categories. Thinking about them as a system makes purchasing and inventory management much easier.

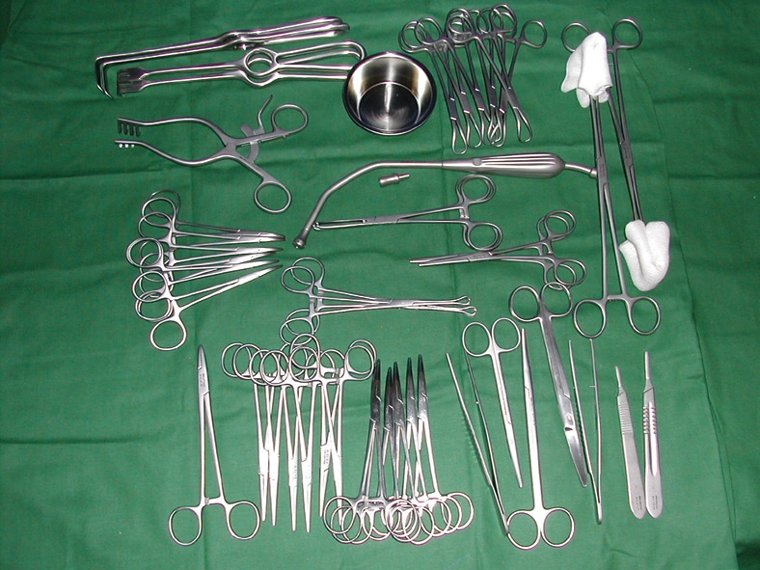
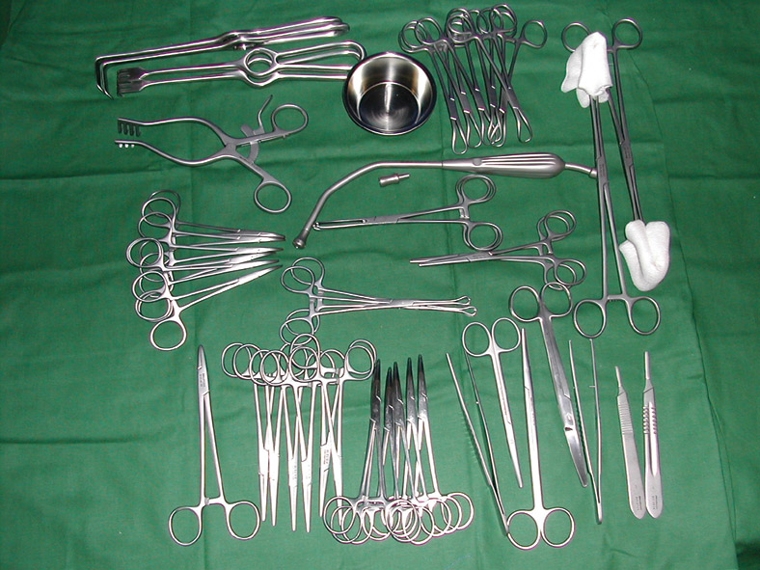
1. Surgical Instruments

Surgical instruments are reusable or, depending on the product, single-use devices designed for specific clinical tasks.

Common categories include:

  • Cutting instruments: surgical scissors, scalpels and blades
  • Grasping instruments: tissue forceps, dressing forceps and atraumatic graspers
  • Clamping instruments: artery forceps, hemostatic clamps and vascular clamps
  • Retracting instruments: handheld and self-retaining retractors
  • Suturing instruments: needle holders and specialized forceps
  • Probing and dilating instruments: probes, dilators and related tools
  • Specialty instruments: orthopaedic, ENT, ophthalmic, gynaecological, laparoscopic and cardiovascular instruments

The important point is that instruments should be selected according to the procedure, not merely by brand name or appearance.

A high-quality instrument that does not match the surgeon’s technique or procedure requirements may be less useful than a correctly specified instrument from another manufacturer.


2. OT Supplies and Equipment

Surgical instruments are only one part of an operating theatre.

OT supplies can include:

  • Operating tables
  • Surgical lights
  • Mayo stands and instrument tables
  • Suction equipment
  • Electrosurgical units
  • Patient monitors
  • Anaesthesia accessories
  • IV stands and accessories
  • Surgical positioning supports
  • Instrument trays
  • Sterile storage systems
  • Waste-management containers

These products form the infrastructure around the procedure.

For example, a surgical light may not physically enter the sterile field, but inadequate lighting can affect visibility and workflow. Similarly, an instrument trolley may appear like a simple piece of furniture, yet its positioning and design influence how efficiently the surgical team works.


3. Surgical Consumables

Consumables are products that are normally used once or replaced frequently.

Typical examples include:

  • Surgical gloves
  • Masks and caps
  • Gowns
  • Drapes
  • Surgical blades
  • Sutures
  • Needles
  • Syringes
  • Gauze and swabs
  • Absorbent pads
  • Adhesive tapes
  • Skin preparation products
  • Suction tubing
  • Electrosurgical accessories
  • Sterile dressings
  • Specimen containers

Consumables deserve particularly careful inventory management because demand can fluctuate significantly with surgical volume.

Running out of a reusable instrument is inconvenient. Running out of a critical disposable during a procedure can be considerably more disruptive.


Surgical Instruments vs OT Supplies vs Consumables

Understanding the difference helps procurement teams build better purchasing strategies.

CategoryExamplesTypical UseMain Purchasing Consideration
Surgical instrumentsForceps, scissors, clampsProcedure-specificQuality, function, durability
OT equipmentSurgical lights, tables, suctionTheatre infrastructureReliability, safety, service
ConsumablesGloves, sutures, bladesUsually single-useSterility, expiry, availability
Sterile processing suppliesPouches, indicators, wrapsReprocessingCompatibility and traceability
Specialty productsLaparoscopic, orthopaedic instrumentsSpecialized proceduresClinical compatibility

The biggest mistake is treating every category as if it follows the same purchasing logic.

A reusable instrument should be evaluated partly on life-cycle value, while a consumable may be evaluated more heavily on cost per procedure, clinical performance, packaging and supply continuity.


How to Choose the Right Surgical Instruments

1. Start With Procedures, Not Catalogues

Before purchasing, create a procedure-wise instrument requirement list.

For example, a general surgery setup may require a different combination of:

  • Scalpels
  • Forceps
  • Retractors
  • Hemostatic clamps
  • Needle holders
  • Suction instruments

than an orthopaedic, ENT or ophthalmic setup.

A practical approach is to create an instrument matrix:

Procedure → Instrument → Quantity → Size → Material → Reprocessing Method → Replacement Cycle

This prevents the common problem of buying large quantities of instruments that are rarely used while understocking frequently required items.


2. Evaluate Instrument Quality Beyond Appearance

Two stainless-steel instruments may look almost identical but perform very differently.

When evaluating surgical instruments, consider:

  • Jaw alignment
  • Locking mechanism
  • Ratchet performance
  • Cutting sharpness
  • Surface finish
  • Corrosion resistance
  • Handle ergonomics
  • Weight and balance
  • Compatibility with sterilization processes
  • Manufacturer’s instructions for use

The FDA classifies surgical forceps and similar devices that contact blood or normally sterile tissue as critical devices, meaning appropriate reprocessing is essential between uses.


Sterilization: The Hidden Backbone of Surgical Safety

A beautifully organized instrument tray is not enough.

The instruments must also undergo appropriate cleaning, disinfection or sterilization according to their intended use and the manufacturer’s instructions.

The CDC emphasizes that effective sterilization depends on proper cleaning first because organic and inorganic material can interfere with subsequent processing.

The FDA similarly describes reusable-device reprocessing as a multistep process that begins with point-of-use treatment and cleaning before the device is disinfected or sterilized and returned to service.

A practical processing pathway

Point-of-use care → Cleaning → Inspection → Packaging → Sterilization → Monitoring → Storage → Distribution

Each step matters.

A damaged instrument may need repair or removal from service. A compromised sterile package should not simply be placed back into the inventory because “the instrument inside looks clean.”

AORN’s current perioperative guidance also emphasizes instrument cleaning, packaging, sterilization and verification as essential elements of reliable sterile processing.


Why Sterile Technique Matters in the OT

Sterile technique is not just about wearing gloves.

It involves controlling the entire environment around the sterile field.

Key considerations include:

  • Surgical hand antisepsis
  • Appropriate gowning and gloving
  • Inspecting sterile packaging
  • Opening sterile supplies correctly
  • Maintaining the sterile field
  • Minimizing unnecessary movement
  • Limiting unnecessary OR door opening
  • Handling sterile items appropriately

AORN’s 2025 guidance highlights the importance of protecting the sterile field and minimizing contamination risks, including unnecessary movement and improper handling of sterile supplies.

The WHO’s surgical-site-infection guidance similarly places infection prevention across the preoperative, intraoperative and postoperative stages rather than treating it as a single isolated activity.


The Most Important Consumables to Keep Under Control

Not every product deserves the same inventory strategy.

A useful method is to divide consumables into three groups:

Critical

Items whose absence could interrupt or seriously affect a procedure.

Examples may include:

  • Procedure-specific sutures
  • Surgical blades
  • Essential sterile drapes
  • Specialty disposable accessories
  • Certain suction or electrosurgical components

High-Use

Items consumed frequently across many procedures.

Examples include:

  • Surgical gloves
  • Masks
  • Gauze
  • Syringes
  • Standard dressings

Specialty / Low-Use

Products required for particular procedures but used less frequently.

These need careful forecasting rather than excessive stock.

This approach can reduce both stockouts and dead inventory.


Surgical Inventory: Think Beyond “How Many Are Left?”

A modern OT inventory system should ideally track more than quantity.

Useful fields include:

Inventory FieldWhy It Matters
Product NameIdentifies the item
CategorySupports purchasing and reporting
ProcedureConnects item to clinical use
SKUEnables accurate stock tracking
Brand/ManufacturerSupports consistency
Pack SizePrevents ordering errors
Sterile/Non-sterileDetermines handling
Lot/BatchSupports traceability
Expiry DateReduces expiry-related waste
Reorder LevelPrevents stockouts
Storage RequirementProtects product integrity

For high-value or critical products, lot and batch traceability can be particularly important.


Reusable vs Single-Use: Which Is Better?

There is no universal answer.

FactorReusableSingle-use
Upfront costHigherUsually lower per unit
ReprocessingRequiredGenerally not required
Long-term economicsPotentially favorableRecurring purchase
WastePotentially lowerHigher
Instrument lifespanDepends on careOne procedure/use
Processing complexityHigherLower
Best suited toDurable instrumentsMany disposable applications

The correct decision depends on the product, procedure, local regulations, validated processing capability and manufacturer’s instructions.

Importantly, a facility should never assume that a product labeled single-use can simply be cleaned and reused. Reprocessing single-use devices is a separately regulated practice in some jurisdictions and requires appropriate controls.


A Smarter Surgical Procurement Checklist

Before ordering surgical instruments or OT supplies, ask:

Clinical

  • What procedure will this product support?
  • Is the size and design appropriate?
  • Does it match the surgeon’s preferred technique?

Quality

  • Is the manufacturer identifiable?
  • Is product documentation available?
  • Does the instrument tolerate the intended processing method?

Infection Control

  • Is the item sterile or non-sterile?
  • What is the validated reprocessing pathway?
  • Are cleaning and sterilization instructions available?

Inventory

  • What is average monthly consumption?
  • What is the minimum stock level?
  • What is the lead time?
  • Does the product have an expiry date?

Financial

  • What is the purchase price?
  • What is the expected service life?
  • What are repair and reprocessing costs?
  • What is the cost per procedure?

This last point is particularly important.

The cheapest surgical instrument is not necessarily the least expensive instrument.

If an inexpensive instrument loses alignment quickly, requires frequent replacement or performs poorly, its true cost may be much higher than the initial invoice suggests.


Common Buying Mistakes to Avoid

Buying Based Only on Price

Price matters, but clinical performance, durability and service support matter too.

Overstocking Every Product

Excess stock can tie up capital and increase expiry risk, particularly with sterile consumables.

Ignoring Sterile Processing Staff

AORN specifically highlights the value of involving sterile-processing personnel in pre-purchase evaluation because they understand cleaning, decontamination, processing equipment and instrument characteristics from an operational perspective.

Mixing Incompatible Products

Not every instrument, tray, sterilization pouch or accessory works optimally with every processing system.

Poor Product Identification

Similar-looking instruments can easily be confused. Standardized names, SKUs, sizes and photographs can make inventory management considerably safer.


The Future of OT Procurement Is Data-Driven

One of the biggest changes in healthcare procurement is the movement from simple stock counting toward procedure-based inventory intelligence.

Imagine an inventory dashboard showing:

Procedure scheduled → Required instrument set → Consumables required → Current stock → Sterile stock available → Reorder requirement

That is far more useful than simply knowing that “50 surgical products” are in the warehouse.

For hospitals and growing surgical centres, connecting ERP, inventory and procurement systems can help identify consumption patterns, reduce emergency purchasing and improve stock availability.

The goal isn’t to keep the maximum amount of inventory.

It is to maintain the right inventory at the right time in the right condition.


Final Thoughts: Build the OT Around Reliability

Surgical instruments may be the visible tools of surgery, but safe operating-room performance depends on an entire ecosystem.

Quality instruments need appropriate cleaning and sterilization. Sterile supplies need correct handling. Consumables need reliable forecasting. Equipment needs preventive maintenance. Inventory needs traceability. And the clinical team needs confidence that the required product will be available when it matters.

WHO guidance emphasizes surgical-site-infection prevention as a system-wide responsibility, while FDA, CDC and AORN guidance reinforces the importance of appropriate device reprocessing, sterile processing and perioperative practice.

For healthcare facilities, the smartest approach is therefore not simply to ask:

“Which surgical instruments should we buy?”

Instead, ask:

“What does our procedure mix require, how will these products be processed and maintained, and how can we guarantee availability without creating unnecessary inventory?”

That shift—from product purchasing to clinical-system thinking—is what turns an ordinary OT supply strategy into a reliable one.

Ready to improve your OT inventory?

Start by auditing your current surgical instruments, procedure-specific sets, critical consumables, sterile-processing workflow and reorder levels. Identify the products that create the most frequent delays or emergency purchases, then standardize those first.

For more healthcare buying guides, explore related resources on medical equipment, laboratory equipment, dental supplies, and orthopaedic products to build a more organized and efficient healthcare procurement system.

Leave a Reply

Your email address will not be published. Required fields are marked *

Related Post

6983515bad2f1546927f65f9 6841b655182dca1cbca49add image1 1

Essential Medical Supplies Every Clinic Should Stock: A Practical Guide for Safer, Smarter Care

Introduction: The Right Supply Can Change the Entire Clinical Workflow Imagine a patient arrives with a minor wound. The clinician is ready, the examination room is prepared, and the diagnosis takes only a few minutes. Then someone realizes the clinic has run out of sterile gauze. It sounds like a small problem. In practice, it can interrupt treatment, delay the next appointment, create unnecessary stress, and compromise workflow. That is why essential medical supplies are not simply items stored in cupboards. They are part of a clinic’s patient-safety infrastructure. A well-stocked clinic does not necessarily have the largest inventory. It has the right products, in appropriate quantities, available when and where they are needed. The World Health Organization (WHO) notes that equipment selection should reflect the facility, available workforce, and local disease burden rather than relying on one universal list. This guide explains what most outpatient and primary-care clinics should consider stocking, how to prioritize purchases, and how to avoid the common mistake of confusing more inventory with better preparedness. What Counts as Essential Medical Supplies? The exact requirements depend on the clinic’s specialty, patient volume, procedures, and local regulations. A general outpatient clinic will have different needs from a dental practice, dermatology clinic, emergency centre, or women’s health facility. However, most clinics can organize their core inventory into several practical groups: This category-based approach is more useful than simply creating a huge shopping list. 1. Infection Prevention and PPE: The First Line of Protection If there is one category a clinic should never treat as an afterthought, it is infection-control supplies. CDC Standard Precautions apply to all patient care and include hand hygiene, appropriate PPE, environmental cleaning, injection safety, and proper handling of reusable equipment. Essential items include: Hand hygiene products deserve special attention. WHO’s “Five Moments for Hand Hygiene” framework emphasizes cleaning hands before patient contact, before aseptic procedures, after body-fluid exposure, after patient contact, and after touching the patient’s surroundings. Practical insight: Do not store sanitizer only at a central nursing station. Put hand-hygiene supplies where clinical decisions happen—near examination areas, treatment rooms, and other points of care. 2. Examination and Diagnostic Supplies A diagnosis begins with good information. Even sophisticated clinical knowledge is limited when basic examination equipment is missing or unreliable. A general clinic should consider maintaining: For frequently used diagnostic equipment, having a backup can be more valuable than purchasing an expensive device that is rarely used. A simple comparison Supply Primary purpose Stock priority Key consideration BP monitor Blood-pressure assessment High Correct cuff sizes Pulse oximeter Oxygen saturation High Accuracy and battery life Thermometer Temperature High Easy cleaning Stethoscope Cardiopulmonary assessment High Durability and acoustics Glucometer Blood glucose testing Medium–High Strip compatibility Examination light Visual examination Medium Brightness and positioning Otoscope Ear examination Specialty-dependent Disposable/reusable tips The important point is that equipment availability should match the clinical services actually offered. WHO similarly emphasizes that medical-device selection should be based on local requirements rather than assuming a universal equipment package. 3. Injection and Medication-Administration Supplies Injection-related products require particularly careful inventory control because availability and infection prevention are closely connected. Common supplies include: Safety is more important than simply buying in bulk. CDC injection-safety guidance states that single-dose vials should not be used for more than one patient, and contaminated or questionable vials should be discarded. Likewise, used sharps should be placed in appropriate puncture-resistant containers rather than being handled casually after use. Inventory lesson: The cheapest syringe is not necessarily the lowest-cost option if poor packaging, inconsistent quality, or unreliable availability creates waste or clinical risk. 4. Wound-Care Supplies Cuts, abrasions, punctures, minor burns, postoperative wounds, and dressing changes are common reasons patients require basic treatment. A clinic’s wound-care stock may include: Instead of keeping one enormous assortment, clinics should analyze the wounds they actually treat. For example, a dermatology clinic may consume more small dressings and sterile swabs, while an urgent-care facility may need a broader range of trauma-related products. 5. Emergency and First-Response Supplies Even a routine outpatient clinic can encounter a medical emergency. The emergency stock should be determined by the clinic’s services, staffing, local protocols, and applicable regulations. Depending on the setting, this may include: The important principle is readiness, not decoration. An emergency trolley filled with expired products or equipment that staff have never practiced using is not a prepared emergency system. Every clinic should periodically verify: 6. Specimen Collection and Point-of-Care Testing Clinics that perform laboratory testing or collect specimens need a separate inventory category. Depending on services, this may include: One frequently overlooked item is labeling material. A test cannot be managed safely if the specimen is collected correctly but identification is incomplete or inaccurate. Therefore, labels, markers, requisition forms, and specimen bags should be treated as clinical supplies—not office stationery. 7. Cleaning, Disinfection and Medical Waste Supplies Clinical inventory does not end at the examination table. Cleaning and waste-management supplies help maintain a safe environment between patients. CDC guidance emphasizes cleaning and disinfecting patient-care environments and ensuring appropriate PPE for cleaning activities. Clinics should assess their need for: The goal is not merely to make rooms look clean. Frequently touched surfaces close to patients can become contaminated and require appropriate cleaning and disinfection. 8. How Much Should a Clinic Keep in Stock? This is where many inventory systems go wrong. Buying six months’ worth of everything may sound safe, but excessive inventory can create expired products, tied-up capital, storage problems, and hidden waste. A better approach is to divide products into three groups: Stock level Examples Suggested approach Critical Gloves, syringes, gauze, hand hygiene products Maintain safety stock Routine Dressings, tapes, examination consumables Reorder based on usage Specialty Procedure-specific products Stock according to scheduled demand A useful starting point is to calculate average monthly consumption and establish a reorder point based on supplier lead time plus a safety buffer. For example: Reorder Point = Average Daily Usage × Supplier Lead Time + Safety Stock This turns inventory management from guesswork into a measurable process.

steptodown.com148887 1024x683 1

Diagnostics: Diagnostic Devices, Laboratory Equipment & Testing Solutions

Introduction: The Test Result Is Only as Good as the System Behind It A blood sample can fit into a tiny tube, but the system required to turn that sample into a trustworthy result can be remarkably sophisticated. Behind a routine CBC, blood glucose test, urine analysis, culture report or molecular test is an entire chain of diagnostic devices, trained professionals, consumables, quality controls, software and laboratory equipment. When even one part of that chain fails, the final result can be delayed, inaccurate or difficult to interpret. The World Health Organization (WHO) describes diagnostics as fundamental to prevention, screening, diagnosis, treatment monitoring and disease surveillance. It also emphasizes that access to diagnostics must include quality across the entire testing value chain—not simply access to a machine or test kit. That leads to an important question for hospitals, diagnostic centres, clinics and laboratories: What makes diagnostic equipment genuinely useful—not merely technologically impressive? The answer lies in matching the right technology to the clinical workload, test requirements, staff capabilities and quality-management system. What Are Diagnostic Devices and Testing Solutions? Diagnostic devices are tools used to detect, measure or monitor physiological conditions and diseases. They range from simple point-of-care devices to highly automated laboratory systems. The U.S. FDA defines in-vitro diagnostics (IVDs) as tests performed on samples such as blood or tissue collected from the body. These tests can support disease diagnosis, treatment decisions and health monitoring. Broadly, diagnostic solutions can be divided into: The key insight is that these categories are interconnected. A modern analyzer cannot compensate for poor sample collection, incorrect storage or inadequate quality control. Laboratory Equipment: The Foundation of Diagnostic Testing A laboratory may have advanced analyzers, but its day-to-day performance depends heavily on supporting laboratory equipment. This includes everything from centrifuges and microscopes to refrigerators, incubators, pipettes and biosafety equipment. Essential Laboratory Equipment Categories Equipment Primary Application Common Laboratory Use Centrifuge Separating sample components Blood, urine and biochemical testing Microscope Visual examination Hematology, microbiology, pathology Hematology Analyzer Blood-cell analysis CBC and differential counts Biochemistry Analyzer Chemical analysis Glucose, liver and kidney parameters Immunoassay Analyzer Antigen/antibody detection Hormones, infections, biomarkers PCR System Molecular detection Infectious diseases and genetic testing Incubator Controlled temperature growth Microbiology and cell-related applications Autoclave Sterilization Laboratory instruments and materials Laboratory Refrigerator Sample/reagent storage Temperature-sensitive materials Water Bath Controlled heating Sample preparation and laboratory procedures Pipettes Accurate liquid handling Almost every laboratory workflow Urine Analyzer Urinalysis Routine diagnostic testing Choosing equipment based purely on brand, price or specifications can be misleading. A better approach is to consider the complete workflow. Diagnostic Devices vs Laboratory Equipment: What’s the Difference? The terms are often used interchangeably, but they are not identical. Diagnostic devices are the broader category. They can include equipment used directly on patients, at the point of care or inside laboratories. Laboratory equipment generally refers to instruments and systems used to process, prepare, analyze or store specimens within laboratory environments. For example, a glucometer can be considered a diagnostic device used near the patient, while a fully automated chemistry analyzer is laboratory equipment. WHO’s Essential Diagnostics List recognizes the importance of having appropriate diagnostic technologies available at different levels of healthcare, including primary-care and laboratory settings. A Simple Comparison Factor Point-of-Care Diagnostics Laboratory Testing Location Near patient Central laboratory Turnaround time Usually rapid Can range from minutes to days Equipment complexity Often lower Moderate to highly sophisticated Testing volume Usually low/moderate Moderate to very high Skilled staff May require limited training Usually trained laboratory personnel Examples Glucose meters, rapid tests CBC, chemistry, PCR, immunoassay Neither approach is universally better. The right choice depends on the clinical question, urgency, patient population and available infrastructure. The Most Important Laboratory Equipment Categories 1. Hematology Equipment Hematology analyzers automate the measurement of blood-cell parameters. A modern analyzer can provide information such as: For busy diagnostic centres, automation can improve throughput and reduce repetitive manual work. However, automation should not eliminate professional oversight. Unexpected results, flags or abnormal patterns may require additional review. 2. Clinical Chemistry Analyzers Clinical chemistry systems measure substances in biological specimens. Common parameters include: For many laboratories, chemistry analyzers are among the highest-utilization instruments, making factors such as reagent availability, throughput, calibration requirements, maintenance and service support particularly important. 3. Microbiology Equipment Microbiology laboratories need equipment designed around contamination control, culture and organism identification. Typical equipment includes: Here, equipment selection is closely linked with biosafety and workflow design. WHO highlights biosafety and biosecurity as integral parts of laboratory quality management. 4. Molecular Diagnostic Equipment Molecular diagnostics have transformed the detection of infectious diseases and genetic conditions. PCR-based systems, for example, can detect specific nucleic-acid sequences and are used across infectious disease and molecular testing applications. More advanced laboratories may also use: The important consideration is not simply buying the newest molecular platform. Laboratories should evaluate test menu, sample volume, reagent availability, turnaround-time requirements and staff competency. 5. Microscopes and Imaging-Based Laboratory Tools Microscopy remains important despite the rise of automation. Depending on the specialty, microscopes can support examination of: In many situations, the microscope remains an excellent example of a technology whose value depends heavily on the operator’s expertise. The Hidden Half of Diagnostics: Sample Management One of the most overlooked parts of diagnostic testing happens before the sample reaches the analyzer. Consider a blood sample. Incorrect patient identification, inappropriate collection, inadequate mixing, delayed transportation or unsuitable storage can compromise the test before analysis even begins. WHO describes laboratory testing as a process involving pre-examination, examination and post-examination stages, all of which require quality management. This means laboratories should pay attention to: WHO’s laboratory quality manual resources specifically include procedures for equipment installation, repair, decontamination, sample labelling, sample acceptance/rejection and result validation. The lesson: buying an advanced analyzer without fixing sample workflow is like installing a powerful engine in a car with poor brakes. How to Choose Laboratory Equipment When evaluating laboratory equipment, use a workflow-first approach. 1. Start With Test Volume Estimate: A small clinic may not need the same automation as a high-volume diagnostic

dentists meeting medical colleagues discussing teeth problems dental clinic young professional doctors studying jaw ray 62382915

For Healthcare Professionals: Practical Insights for Dentists, Doctors, Clinics & Hospitals

Picture this: a small dental practice spends years building trust with its patients, one cleaning and one kind word at a time. Then one morning, its website — the same one that quietly collects appointment requests and new-patient forms — gets flagged for serving malware. Within a week, patient records are for sale on a forum neither the dentist nor her office manager has ever heard of. This isn’t a rare horror story anymore. It’s Tuesday. For healthcare professionals, the website has quietly become one of the most exposed parts of the practice — and most clinics never planned for that. This post breaks down what’s actually happening, how it compares across practice types, and what you can do about it this month, not “eventually.” Why This Is Suddenly Everyone’s Problem Healthcare has held the unwanted title of the costliest industry for data breaches for 14 straight years, with the average incident now running $7.42 million. That number sounds like a hospital-only problem — it isn’t. Small practices, dental offices, and single-location clinics get swept into the same statistics because attackers don’t discriminate by practice size; they discriminate by how easy the target is. The shift in attack methods matters just as much as the cost. Hacking and IT-related incidents now account for more than 80% of large healthcare breaches, up from roughly half that share back in 2019. Ransomware alone drives nearly half of all confirmed healthcare breaches in 2026, and for the first time in nearly two decades of tracking, exploiting unpatched software vulnerabilities has overtaken stolen passwords as the top way attackers get in. That detail matters enormously for anyone running a website on a content management system that needs regular updates. The Comparison: Where Different Practices Are Exposed Not every healthcare setting carries the same risk profile. Here’s a practical breakdown of where the pressure points typically sit. Practice Type Common Website Function Typical Weak Point Priority Fix Solo dental/medical practice New patient intake forms, appointment requests Outdated CMS plugins, no BAA with host Patch management + compliant hosting Multi-location clinic Booking systems, provider portals Inconsistent access controls across sites Centralized, role-based access Specialty/therapy practice Secure messaging, telehealth links Third-party embeds without vendor agreements Vendor risk review + signed BAAs Hospital system EHR integration, patient portal Business associate exposure, legacy systems Third-party monitoring + audit logging Third-party vendors deserve special attention here. Business associates are now named in roughly one in three reported healthcare breaches, and that share has doubled in a single year. If your website hands appointment data, chat widgets, or analytics to an outside company without a signed Business Associate Agreement, that gap is treated by regulators as its own violation — not a minor technicality. Key Insight #1: Your Website Platform Wasn’t Built for PHI, and That’s Fine — If You Know It A huge share of clinic and practice websites run on WordPress, which is understandable: it’s flexible, familiar, and inexpensive. But it’s worth being clear-eyed about a specific point that trips up a lot of practices — WordPress is not HIPAA-compliant out of the box. Compliance isn’t a feature you install; it’s a property of how the whole environment — hosting, plugins, forms, and vendor contracts — is configured and maintained together. That doesn’t mean healthcare organizations should avoid WordPress. It means treating any part of the site that touches protected health information (appointment forms, secure messaging, patient portals) differently from the marketing pages describing your services. One widely echoed piece of advice from web architects working in healthcare is refreshingly simple: don’t store sensitive patient information directly inside WordPress at all — route it instead to purpose-built, compliant systems designed to hold that data securely. Key Insight #2: Hosting Is the Foundation, Not an Afterthought If there’s one decision that quietly determines your entire security posture, it’s who hosts your site. Standard consumer hosting — the kind marketed on price and ease of setup — typically will not sign a Business Associate Agreement or meet PHI protection standards like encryption at rest and audit logging. A healthcare website deserves the digital equivalent of the physical security you already apply to paper charts in a locked filing cabinet. Practical signs your hosting is doing its job: Key Insight #3: Multi-Factor Authentication Is the Cheapest Insurance You’ll Ever Buy Ask any security consultant working with clinics what single change stops the most incidents, and multi-factor authentication comes up almost every time — particularly for anything resembling a patient portal or staff login. It costs little, takes minutes to enable, and closes off the majority of credential-based attacks that once dominated the threat landscape. Given that external actors are behind roughly two-thirds of confirmed healthcare breaches, and financial motives drive the vast majority of them, making stolen credentials useless on their own is one of the highest-leverage moves a small practice can make. Key Insight #4: The Detection Gap Is Longer Than You’d Think Healthcare breaches take an average of 279 days to identify and contain — the longest of any industry tracked. Translate that into practice terms: a compromise discovered today may have been sitting quietly since roughly last spring. This is precisely why routine monitoring, logging, and even a simple quarterly review of who has admin access to your website matter more than a one-time security push. Set-and-forget security is, in practice, forget-and-regret. What This Means for Your Practice, Starting This Month None of this requires a hospital-sized IT budget. A realistic starting checklist looks like: A Final Word The trust patients place in a dental chair or an exam room extends, whether we’ve fully reckoned with it or not, to the “Book an Appointment” button on the website. Protecting that trust isn’t about becoming a cybersecurity expert overnight — it’s about treating your digital front door with the same seriousness as your physical one. If this rundown raised questions about your own practice’s setup, that’s worth sitting with rather than shrugging off. Talk to your web host today
