
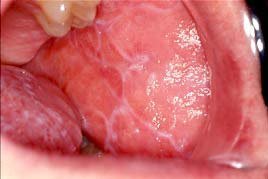
oral lichen planus 1

Understanding Oral Lichen Planus: Causes, Symptoms & Treatment

Category: Dental — Oral Medicine & Mucosal Conditions   |   Medical Specialist: Dentist; oral medicine specialist; dermatologist or physician when indicated   |   References: AAOM; ADA; NIDCR Introduction: When a “White Patch” Is More Than a White Patch A white, lace-like pattern inside the cheek can look harmless. Sometimes it is. But when those white lines persist, become sore, or appear alongside red, raw areas, they may point to a condition that deserves professional attention. Oral Lichen Planus (OLP) is a chronic inflammatory condition affecting the tissues inside the mouth. It can be painless and easy to overlook—or painful enough to make eating, brushing, and even speaking uncomfortable. The challenge is that it can resemble several other oral conditions, which is why recognizing the pattern is only the first step. The good news? Oral lichen planus can usually be managed. The goal is not simply to make a lesion “disappear,” but to control inflammation, relieve symptoms, identify possible triggers, protect oral health, and monitor persistent or changing areas over time. Important: Oral lichen planus should be diagnosed by a qualified dentist, oral medicine specialist, dermatologist, or physician. A persistent mouth lesion should not be self-diagnosed. What Is Oral Lichen Planus? Oral lichen planus is a chronic inflammatory disorder involving the oral mucosa. It is generally considered an immune-mediated condition in which immune cells, particularly cytotoxic T cells, attack cells within the oral epithelium. However, the exact trigger behind this immune response remains uncertain. Unlike a contagious infection, oral lichen planus cannot be passed from one person to another. It may occur on its own or alongside lichen planus affecting the skin or other mucosal surfaces. Interestingly, the mouth can sometimes be the only affected area. Common Areas Affected OLP may involve: The inside of the cheeks is particularly characteristic, especially when lesions appear symmetrically. What Causes Oral Lichen Planus? This is one of the frustrating aspects of OLP: there is usually no single identifiable cause. Researchers believe that an abnormal immune response plays the central role. Instead of protecting oral tissues, immune cells target epithelial cells, producing chronic inflammation. Several factors may contribute to or resemble OLP: 1. Immune-System Activity OLP is strongly associated with a T-cell-mediated inflammatory response. In many patients, however, the reason this response begins remains unknown. 2. Medications Some medicines can produce oral lichenoid reactions, which can look remarkably similar to oral lichen planus. Potentially associated medications include certain: This distinction matters because a medication-related lichenoid reaction may improve after the responsible drug is identified and appropriately changed under medical supervision. 3. Dental Materials and Contact Reactions In some cases, oral lichenoid lesions develop near dental restorations or in response to contact allergens. Materials such as metals, resins, or certain ingredients in oral-care products can occasionally be involved. That does not mean every person with OLP needs dental fillings removed. Removing restorations without evidence of a relevant contact reaction is unlikely to cure OLP. 4. Stress and Local Trauma Psychological stress and local mechanical irritation may aggravate existing lesions in some individuals. This is better understood as a potential trigger or exacerbating factor rather than a proven underlying cause. 5. Other Associations Hepatitis C has been associated with lichen planus in some populations, although the strength of this relationship varies geographically. Your clinician can decide whether additional medical evaluation is appropriate based on your individual history. Oral Lichen Planus Symptoms: What Does It Look and Feel Like? OLP does not look the same in everyone. Some people have no discomfort at all, while others experience significant burning and soreness. Common Signs and Symptoms Look out for: The classic white, branching lines are called Wickham striae. They are one of the visual clues clinicians may recognize during an oral examination. The Erosive Form Can Be More Painful Erosive oral lichen planus can produce red areas, superficial erosions, and ulceration. The gums may become particularly uncomfortable, sometimes producing a pattern known as desquamative gingivitis, where the surface tissue becomes red and peels away. This is where OLP can stop being a cosmetic concern and become a quality-of-life issue. Imagine trying to eat citrus fruit when the lining of your mouth is already inflamed. For someone with erosive OLP, that everyday experience can be surprisingly painful. Oral Lichen Planus vs Other Common Mouth Lesions Not every white or red oral lesion is OLP. Several conditions can look similar. Condition Typical appearance Pain Key consideration Oral Lichen Planus Lacy white lines, plaques, red/erosive areas Variable Often chronic and may be symmetrical Oral Thrush Creamy white patches Often burning Usually associated with Candida infection Leukoplakia Persistent white patch Often painless Requires professional evaluation Canker sore Localized ulcer Often painful Usually heals within a limited period Oral lichenoid reaction Similar to OLP Variable May relate to medication or contact exposure Oral cancer Persistent ulcer, lump, red/white lesion or other change May be painless Requires prompt assessment The important takeaway is simple: appearance alone cannot always establish the diagnosis. How Is Oral Lichen Planus Diagnosed? Diagnosis usually begins with a detailed oral examination and medical history. Your clinician may ask about: Why Is a Biopsy Sometimes Necessary? A biopsy may be recommended when the appearance is unusual, the diagnosis is uncertain, or an area needs to be evaluated for another condition. Microscopic examination can support the diagnosis and help distinguish OLP from other lichenoid conditions. Biopsy can also be important when clinicians need to rule out dysplasia or oral cancer. This is an important distinction: a biopsy does not mean your dentist thinks you have cancer. It is often a diagnostic safety step. Oral Lichen Planus Treatment: What Actually Helps? There is currently no guaranteed permanent cure for every case of OLP. Treatment is generally focused on controlling inflammation and symptoms while monitoring the condition. 1. Topical Corticosteroids For symptomatic oral disease, topical corticosteroids are commonly used and are considered a mainstay of treatment. They may be delivered as: More severe disease may require additional therapies. Because prolonged steroid use inside the mouth can
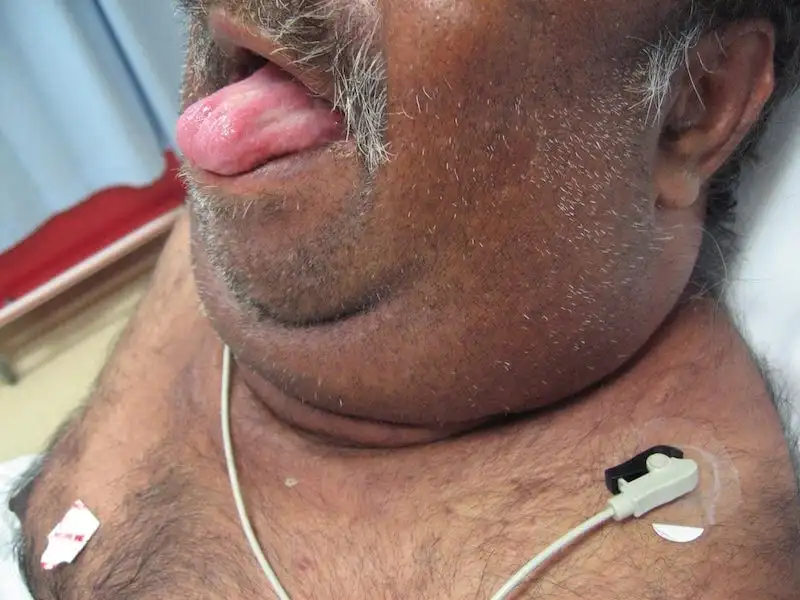
ENT Equivocation 003 Ludwig angina

Understanding Ludwig’s Angina: Causes, Symptoms & Treatment

Category: Dental — Oral Surgery & Pathology   |   Medical Specialist: Oral and maxillofacial surgeon; oral medicine/oral pathology specialist; dentist   |   References: AAOMS; ADA; NIDCR Introduction: When a Tooth Infection Becomes an Emergency A toothache may seem like a problem that can wait until tomorrow. But when a dental infection begins spreading beneath the tongue and into the neck, the situation can change rapidly. Ludwig’s Angina is a rare but potentially life-threatening bacterial infection involving the floor of the mouth and the spaces beneath the jaw. Unlike a typical dental abscess, it can spread through interconnected tissue spaces and push the tongue upward, threatening the airway. That is what makes Ludwig’s Angina particularly important for both patients and dental professionals: the biggest danger isn’t simply the infection—it is the swelling that can interfere with breathing. Modern antibiotics, advanced imaging and better airway management have dramatically improved outcomes. Yet the condition still requires urgent medical attention because deterioration can occur quickly. Emergency warning: Difficulty breathing or swallowing, drooling, rapidly increasing swelling under the jaw or tongue, or a muffled/altered voice should be treated as an emergency. Do not wait for a routine dental appointment. What Is Ludwig’s Angina? Ludwig’s Angina is a rapidly spreading cellulitis, meaning inflammation and infection of soft tissues rather than a simple, well-contained abscess. It classically involves three connected anatomical spaces: The infection can cause firm swelling of these tissues and elevate the tongue. Because the tissues around the airway have limited room to expand, swelling can eventually make breathing difficult. The condition was first described in 1836 by German physician Wilhelm Friedrich von Ludwig. Despite its name, Ludwig’s Angina has nothing to do with the heart condition commonly called angina. What Causes Ludwig’s Angina? Dental infections are the leading cause One of the most important insights about Ludwig’s Angina is that a serious neck infection can begin with something as ordinary as an untreated dental infection. In particular, infections involving the lower second and third molars are strongly associated with Ludwig’s Angina. Current clinical references report that odontogenic infections account for the large majority of cases. Why do these teeth matter? The roots of lower molars can lie close to, or below, the attachment of the mylohyoid muscle. This anatomical relationship provides a pathway through which infection can spread into the submandibular tissues. Common dental sources include: Other possible causes Although dental infections dominate, Ludwig’s Angina can occasionally develop after: The infection is usually polymicrobial, meaning several types of bacteria may be involved. Aerobic and anaerobic organisms—including Streptococcus, Staphylococcus and anaerobic bacteria such as Bacteroides—can contribute. Who Is at Higher Risk? Ludwig’s Angina can occur in otherwise healthy people, but certain factors can increase susceptibility or make infection more difficult to control. Risk factors include: This is one reason preventive dental care matters beyond protecting teeth. Treating an infected tooth early can sometimes prevent a localized dental problem from becoming a deep neck infection. Ludwig’s Angina Symptoms: What Should You Watch For? Early symptoms can resemble an ordinary dental infection, which makes recognition especially important. Common symptoms Patients may experience: A characteristic finding is firm, bilateral swelling around the submandibular and submental areas, sometimes described as a “bull neck” appearance. The red flags matter most Not every symptom carries the same level of urgency. Symptom/sign What it may indicate Urgency Toothache with localized swelling Dental infection Prompt dental assessment Fever + jaw/neck swelling Spreading infection Urgent medical assessment Difficulty swallowing Increasing floor-of-mouth swelling Emergency Drooling Difficulty managing secretions Emergency Tongue elevation/swelling Airway displacement Emergency Muffled or altered voice Possible upper-airway involvement Emergency Difficulty breathing or stridor Threatened airway Immediate emergency care The evidence-based approach is straightforward: airway concerns take priority over diagnostic imaging or routine dental treatment. Why Ludwig’s Angina Can Become Dangerous So Quickly The anatomy of the floor of the mouth explains much of the danger. Think of the neck as a series of connected compartments. An infection does not necessarily remain where it started. It can travel along tissue planes, causing inflammation and swelling in neighboring spaces. As swelling increases, the tongue may be pushed upward and backward. The surrounding tissues can also become increasingly stiff and swollen. This creates a dangerous sequence: Dental infection → tissue-space spread → floor-of-mouth swelling → tongue elevation → airway narrowing → breathing difficulty That progression is why Ludwig’s Angina is considered a medical emergency rather than simply a severe dental infection. Ludwig’s Angina vs. a Typical Dental Abscess These conditions can start from the same dental problem, but their clinical behavior is different. Feature Typical Dental Abscess Ludwig’s Angina Main location Tooth/gum or localized tissue Floor of mouth and submandibular spaces Swelling Usually localized Often firm and more diffuse Airway risk Usually low Potentially life-threatening Tongue elevation Uncommon Characteristic concern Difficulty swallowing May occur Common Breathing difficulty Uncommon Major warning sign Treatment Dental source control ± antibiotics Airway management + IV antibiotics ± surgery The key lesson is that a dental infection should never be judged only by how painful the tooth feels. The location and direction of swelling can be much more important. How Is Ludwig’s Angina Diagnosed? Diagnosis is primarily clinical. A healthcare professional examines the mouth, tongue, jaw and neck while assessing the patient’s ability to breathe and manage secretions. Imaging A contrast-enhanced CT scan of the neck can help determine how far the infection has spread and whether an abscess has developed. However, imaging should not delay airway management in someone whose breathing is threatened. A patient who cannot safely lie flat or manage secretions may need immediate airway intervention rather than being sent for a scan first. Ultrasound may also be useful in selected situations, particularly when clinicians need additional information without immediately sending an unstable patient for CT. Ludwig’s Angina Treatment Treatment is typically carried out in a hospital and involves several teams, often including emergency medicine, anesthesiology, oral and maxillofacial surgery, ENT and critical care. 1. Protect the airway first This is the most important principle. If swelling threatens